GHANA MOVES TO END “NO BED” EXCUSE AS NEW DIGITAL SYSTEM TRACKS MORE THAN 5,000 HOSPITAL BEDS IN REAL TIME

Ghana is piloting a real-time hospital bed and referral management system aimed at reducing the recurring “No Bed Syndrome.” The platform allows emergency teams to see available beds before transporting patients, monitors ambulance movements and tracks patients who remain in emergency beds for more than 24 hours. More than 650 hospitals and 5,000 beds have already been captured, with a wider regional and district rollout planned.
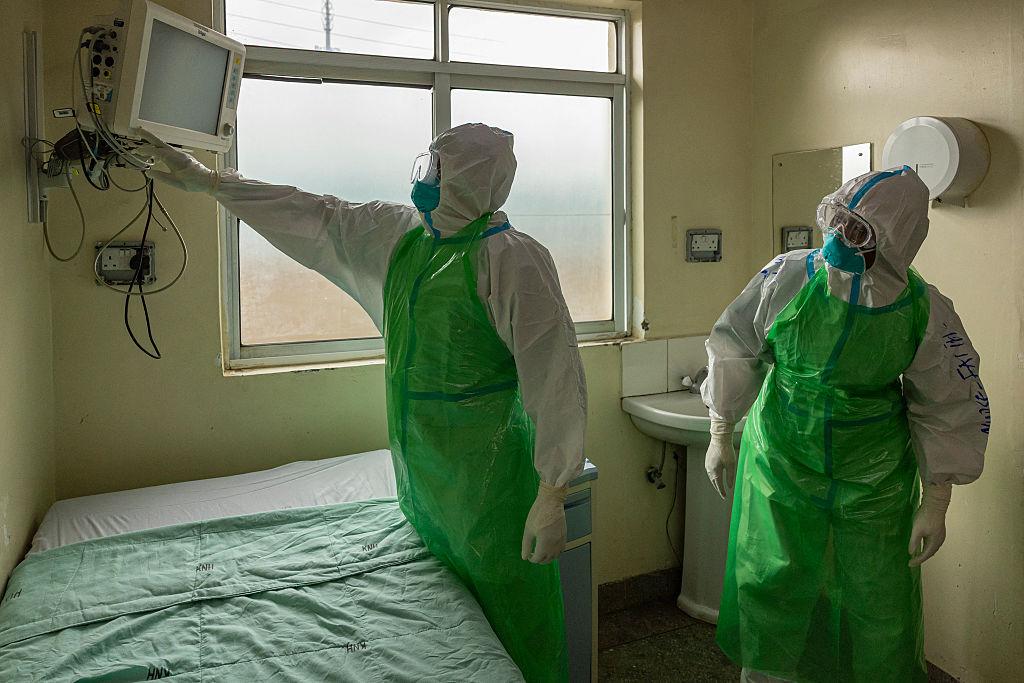
Ghana’s Ministry of Health is rolling out a national digital bed-management and referral system designed to tackle the country’s persistent “No Bed Syndrome” by allowing emergency teams to see available hospital beds in real time before patients are transported from one facility to another. Health Minister Kwabena Mintah Akandoh inspected the National Command Centre for Bed and Referral Management at the Greater Accra Regional Hospital this week, where officials demonstrated a platform capable of displaying bed availability, emergency-unit occupancy and ambulance movements across participating hospitals. More than 650 health facilities have already been captured in the database and over 5,000 beds have been mapped, according to officials overseeing the programme.
The system is intended to address one of the most frustrating weaknesses in Ghana’s emergency referral network, where critically ill patients can be transported to a hospital only to be told that no bed is available and then moved again while their condition deteriorates. Under the new arrangement, dispatchers and Emergency Medical Technicians can check which facility has the appropriate bed and medical capacity before an ambulance begins transporting the patient. The platform is also designed to consider the type of care required and the distance between the patient and suitable facilities rather than merely identifying any empty bed.
Akandoh said the underlying problem is not always that Ghana has absolutely no hospital bed available but that facilities and ambulance teams have lacked a coordinated way of knowing where beds are available at any particular moment. He said the new system gives authorities direct visibility into emergency departments and could reduce situations in which one hospital is overwhelmed while another nearby institution has capacity. The minister has said he can now access a screen from his own office showing emergency-bed conditions at participating institutions, allowing officials to question situations in which a patient is rejected even though another hospital has available space.
The Greater Accra Regional Hospital is currently serving as the central command location for the pilot, with Korle Bu Teaching Hospital, the University of Ghana Medical Centre and other major facilities connected to the system. The pilot also involves the National Ambulance Service, which has been training dispatchers and Emergency Medical Technicians to use the platform during referrals. Ten ambulances in Greater Accra and another ten in the Ashanti Region are currently supporting the pilot, giving authorities an opportunity to test the system before a broader national expansion.
The Ministry of Health says the next stage will involve extending the system to all regional hospitals before moving into district-level facilities. That means the current platform should not yet be interpreted as a fully completed nationwide solution because implementation remains in phases. However, the scale of the database already established shows the government is attempting to build a national referral network rather than a platform serving only a handful of hospitals in Accra.
Officials say the platform does more than identify vacant beds. It can also monitor how long emergency patients remain on particular beds, allowing administrators to identify cases where patients remain in emergency units for more than 24 hours and investigate why they have not been transferred, admitted to an appropriate ward or discharged. This could help hospitals identify bottlenecks inside their own systems rather than simply reporting that the emergency department is full.
The approach is significant because Ghana’s bed shortage is partly a capacity problem and partly a coordination problem. Ghana Health Service Director-General Dr Samuel Kaba Akoriyea said earlier this month that Ghana has roughly one hospital bed for every 1,000 people, compared with a World Health Organization benchmark of around five beds per 1,000 population cited by the GHS. He nevertheless argued that simply purchasing more beds would not solve the problem unless patients could be directed to facilities with the right personnel, equipment and available capacity.
The government is therefore combining digital coordination with plans to increase physical emergency capacity at several major institutions. Akandoh has said expansion measures are being considered at Korle Bu Teaching Hospital, Komfo Anokye Teaching Hospital, Greater Accra Regional Hospital, 37 Military Hospital and Tamale Teaching Hospital. That approach acknowledges that digital visibility can make existing beds more efficient but cannot replace investment where there is a genuine shortage of emergency and critical-care capacity.
The “No Bed Syndrome” has remained politically and emotionally sensitive because delays in obtaining emergency admission have previously been linked to deaths. Earlier in 2026, public debate intensified after 29-year-old engineer Charles Amissah reportedly died after being turned away from multiple hospitals because beds were said to be unavailable. Korle Bu Board Chairman Professor Titus Beyuo subsequently told Parliament that the government was already developing an integrated bed-management and referral system and said information technology would allow health authorities to determine what types of beds were available in individual hospitals in real time.
The digital programme has been under development for several months rather than being created only after this week’s ministerial inspection. A three-day training programme on the National Integrated Bed Management and Referral Coordination System was held in Accra in July, bringing together the Greater Accra Regional Hospital, Korle Bu, UGMC and National Ambulance Service. Later that month, 129 Emergency Medical Technicians completed specialised training covering dispatch consoles, ambulance pickups, bed searches, hospital status boards and referral procedures.
National Ambulance Service leadership also visited Ridge in early October to evaluate the platform before its wider rollout. The service said the system relies on designated personnel inside hospitals to update bed occupancy and service availability continuously so emergency teams receive current rather than outdated information. That requirement will be crucial because a sophisticated digital dashboard becomes unreliable if hospitals fail to update it promptly when a patient is admitted, transferred or discharged.
Officials will therefore need to ensure that every connected facility treats bed-status updates as an operational responsibility rather than an optional administrative task. The technology can only reduce unnecessary ambulance movements if data from participating wards remain accurate. A bed incorrectly listed as available could cause exactly the kind of failed referral the system is supposed to prevent, while beds left marked as occupied after discharge could artificially reduce the capacity visible to dispatchers.
Coordination between referring and receiving facilities is another major issue. National Ambulance Service officials have warned that real-time bed visibility alone will not solve referral failures without clear communication between the hospital sending a patient, the facility expected to receive the patient and the ambulance team responsible for the transfer. The system is therefore being developed as a referral-coordination platform rather than merely a national spreadsheet showing empty beds.
The potential benefits are particularly important for emergency conditions in which minutes matter. Stroke, severe trauma, obstetric emergencies, heart attacks, respiratory failure and other critical conditions can worsen rapidly when ambulances spend time moving between hospitals in search of admission. Matching a patient with an appropriate receiving facility before departure could reduce those delays and allow doctors at the destination to prepare for the patient’s arrival.
The system could also provide policymakers with a clearer picture of where Ghana’s real bed shortages are located. If the dashboard consistently shows particular hospitals operating above safe capacity while beds elsewhere remain underused, managers can reconsider referral patterns and resource allocation. If an entire region repeatedly has no appropriate emergency beds available, the same data would strengthen the case for physical expansion rather than assuming poor coordination is the only problem.
Akandoh has presented the project as part of a broader effort to modernise Ghana’s emergency healthcare system. The government is attempting to link hospitals, ambulance stations and referral teams through one digital infrastructure, creating a national overview that has historically been difficult to achieve in a health system where facilities often manage capacity independently.
The programme will now face the more difficult stage of nationwide implementation. Connecting hundreds of hospitals requires stable internet connectivity, properly trained staff, reliable power, standard operating procedures and clear accountability when facilities fail to update their data. Rural and district hospitals may face very different technological challenges from major teaching hospitals in Accra and Kumasi.
There is also the question of whether the system can remain functional after its initial political and administrative attention fades. Many public-sector technology projects work effectively during pilots but deteriorate later because equipment is not maintained, software is not updated or trained personnel are transferred. Long-term financing and institutional ownership will therefore be as important as the initial rollout.
For patients, however, the goal is straightforward. Someone experiencing a medical emergency should not have to be driven from hospital to hospital simply because the ambulance crew does not know where an appropriate bed exists. The government is betting that a national command system providing real-time visibility can reduce that uncertainty substantially.
The latest inspection shows that the project has moved beyond planning. More than 650 facilities have been entered into the system, over 5,000 beds have been mapped, trained ambulance personnel are participating in the pilot and a command centre is operating at the Greater Accra Regional Hospital. What remains to be demonstrated is whether those tools can consistently translate into faster admission and fewer patients hearing the words “no bed” during life-threatening emergencies.